
StraightSmile Solutions®

The Power of Orthodontic and Myofunctional Therapy Collaboration
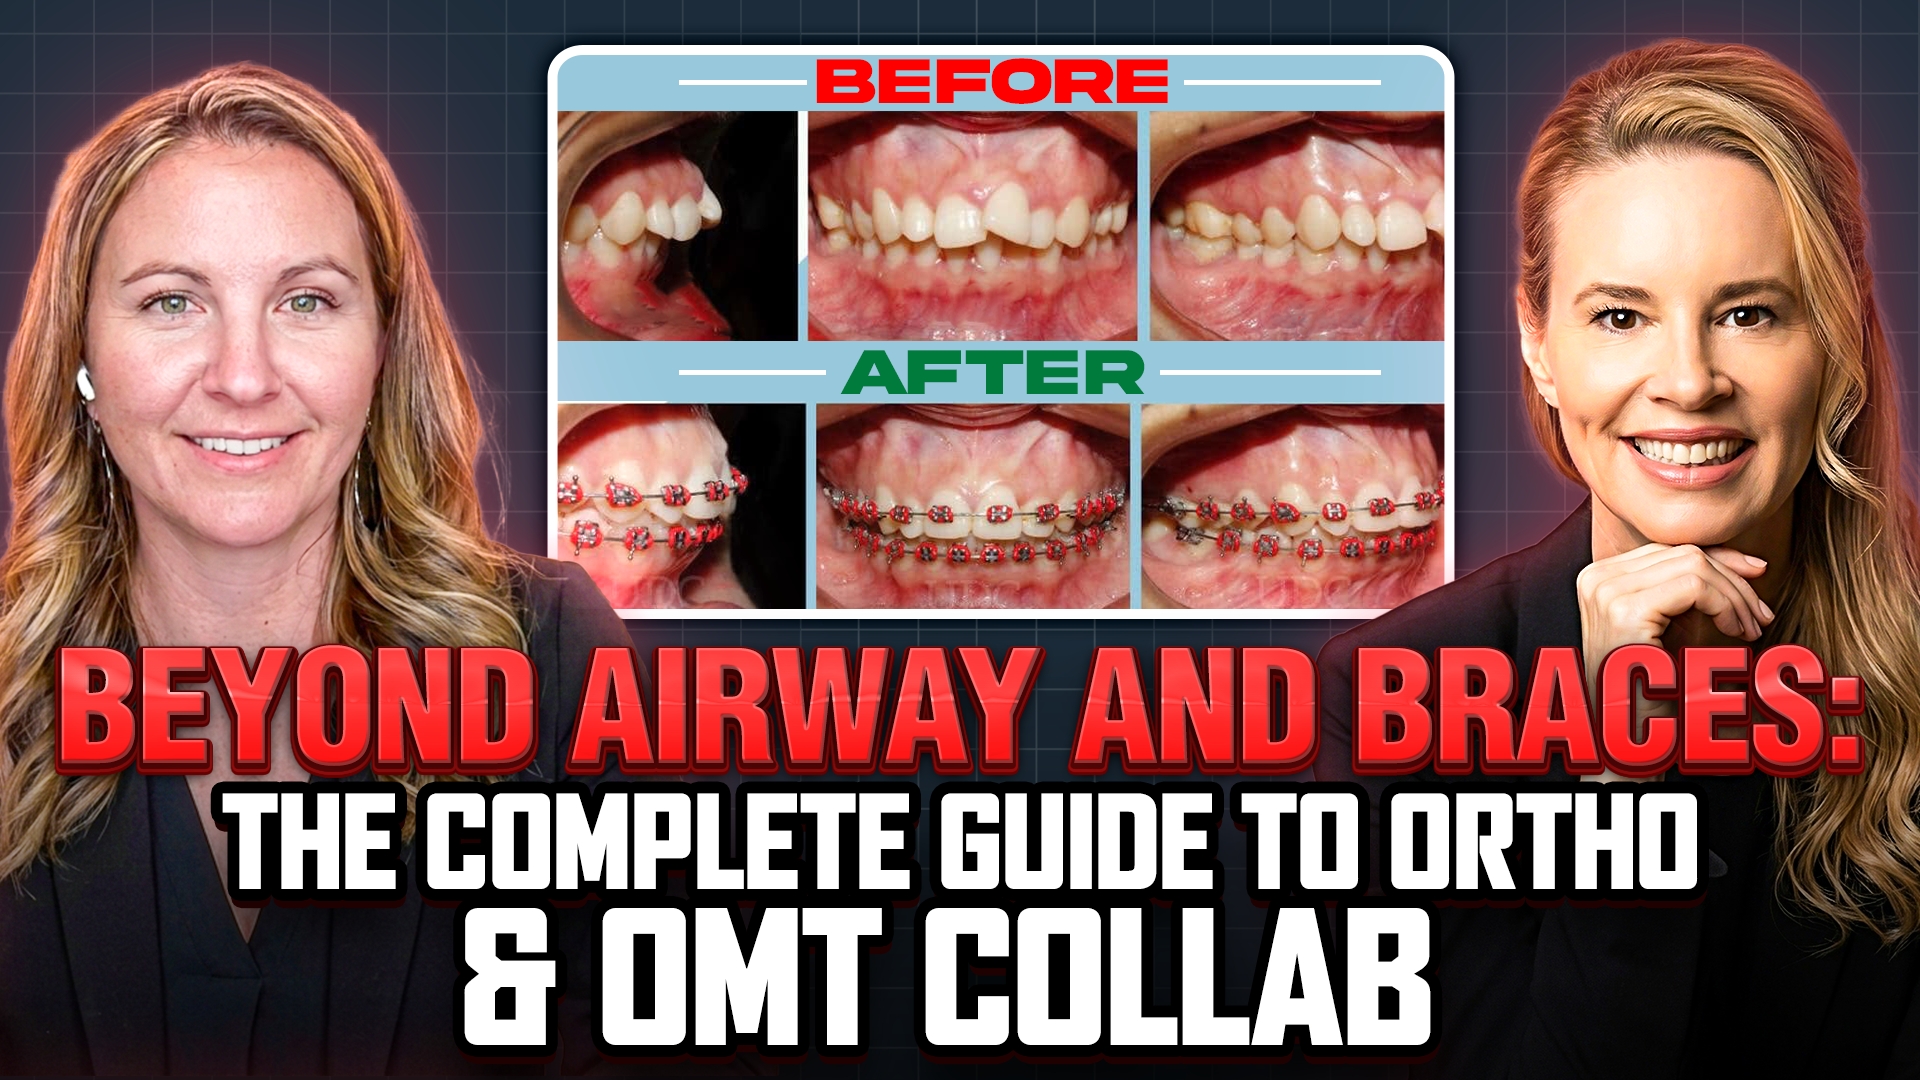
Integrating oral myofunctional therapy into a dental or orthodontic practice marks a vital shift toward a full-body wellness approach to patient care. For decades, traditional orthodontic programs relied on limited techniques, like holding a sugar-free lozenge against the roof of the mouth, or resorting to aggressive fixed habit appliances to control a tongue thrust. However, these localized options rarely address the root neuromuscular dysfunction, leading to compromised facial growth and frustrating orthodontic relapses. A progressive approach treats the oral cavity not as an isolated structure, but as an interconnected system where muscular function directly dictates bone structure and airway health.
Discovering the true depth of this connection often requires a provider to experience the diagnostic process firsthand. Comprehensive myofunctional evaluations go far beyond checking whether a patient can stick out their tongue. Instead, therapists look at functional movement, lateralization compensations, and how a restricted range of motion pulls on the floor of the mouth and strains neck muscles. When these tissues are anchored incorrectly, the body compensates throughout the entire upper cervical region. This structural strain explains why patients struggling with an undiagnosed tongue tie or tongue thrust frequently suffer from severe, long-term temporomandibular joint issues, chronic migraines, and neck stiffness.
True clinical success demands a highly collaborative, interdisciplinary network where the myofunctional therapist acts as the quarterback for the patient’s care. Resolving complex issues often requires coordinating specialized treatments with upper cervical chiropractors to address head and neck alignment, and periodontists trained in specialized functional frenuloplasties. This teamwork is especially vital because adult patients have a lifetime of improper muscle patterning to unravel before they are ready for a surgical release. By strengthening the oral muscles and establishing correct resting postures before and after orthodontic treatment, clinicians can deliver stable structural results, eliminate chronic pain cycles, and fundamentally transform a patient’s systemic health.

Dentistry as a Side Hustle: Do You Have What It Takes?

Dentistry as a Side Hustle: Do You Have What It Takes?
Transitioning your clinical dental expertise into a secondary business venture or consulting role is an achievable goal, but it demands a specific set of foundational traits to succeed. Many professionals explore dental consulting or educational lecturing to diversify their income and scale their industry impact. However, the reality of managing a side business alongside a primary clinical schedule requires intense discipline. It is not a path suitable for everyone, as the baseline demands of entrepreneurship differ vastly from the structured environment of day-to-day patient care.
To thrive in the competitive landscape of professional dental consulting, an individual must possess an extreme, hyper-focused Type A personality. This high level of organization and drive is non-negotiable for balancing strict schedules, content creation, and client communications. Alongside this personality structure, absolute grit and a resilient mindset are mandatory. Publicly putting yourself out there through lecturing, digital media, or business consulting naturally invites criticism, skepticism, and occasional professional pushback. Developing a thick skin and remaining completely indifferent to negativity is the only way to avoid burnout and keep moving forward.
Finally, the unspoken backbone of any high-performing dental side hustle is having a reliable, unconditional family support system. Building an independent brand or consulting firm brings unpredictable financial cycles, stretching from highly lucrative periods to challenging, quiet periods. Having a family that backs your vision through every structural hurdle provides the stability needed to take calculated business risks. When extreme organizational drive, mental resilience, and solid domestic backing align, transforming your specialized clinical knowledge into a profitable secondary venture becomes entirely possible.

Adult Tongue-Tie Release: A Doctor’s Personal Journey

Adult Tongue-Tie Release: A Doctor’s Personal Journey
Undergoing an adult tongue-tie release, or frenectomy, is a profound reminder of how deeply connected our oral anatomy is to overall bodily health. Many dental professionals screen for tongue thrusts, airway constraints, and tethered oral tissues to prevent orthodontic relapse, yet these identical conditions often go unnoticed in ourselves. For adults who grew up before these screenings were commonplace, living with a severe tongue tie can lead to a lifetime of compensation. Navigating this path involves far more than a simple surgical procedure; it requires a dedicated, multidisciplinary timeline spanning months of preparation and highly disciplined post-operative compliance.
A truly successful lingual release relies on a collaborative team consisting of an oral myofunctional therapist, a specialized periodontist, and a cervical chiropractor. This comprehensive approach is essential because the fascia connecting the tongue to the floor of the mouth is completely interrelated with the cervical spine. Clinicians must complete months of targeted myofunctional exercises just to qualify for the surgery, proving they can properly suction and hold the tongue to ensure surgical access. The actual procedure can take nearly an hour, requiring the patient to actively hold difficult tongue positions while completely numb, making the surgery quite demanding for both the patient and the practitioner.
The recovery period immediately following a comprehensive release is notoriously intense, often requiring several days of complete rest and isolation from normal speaking obligations. Because the tongue is exceptionally vascular, standard post-operative anti-inflammatory choices may be limited, making the first week of eating, drinking, and talking a significant hurdle. However, the long-term benefits can be life-changing for chronic sufferers. Patients frequently report an immediate resolution of debilitating, lifelong symptoms, including severe morning jaw pain, chronic tension headaches, and neck stiffness. By restoring full range of motion to the tongue and aligning the cervical spine, adults can experience dramatic improvements in sleep quality, daytime energy levels, and overall systemic relief.

Diagnosing CR-CO Functional Shifts in Orthodontic Patients
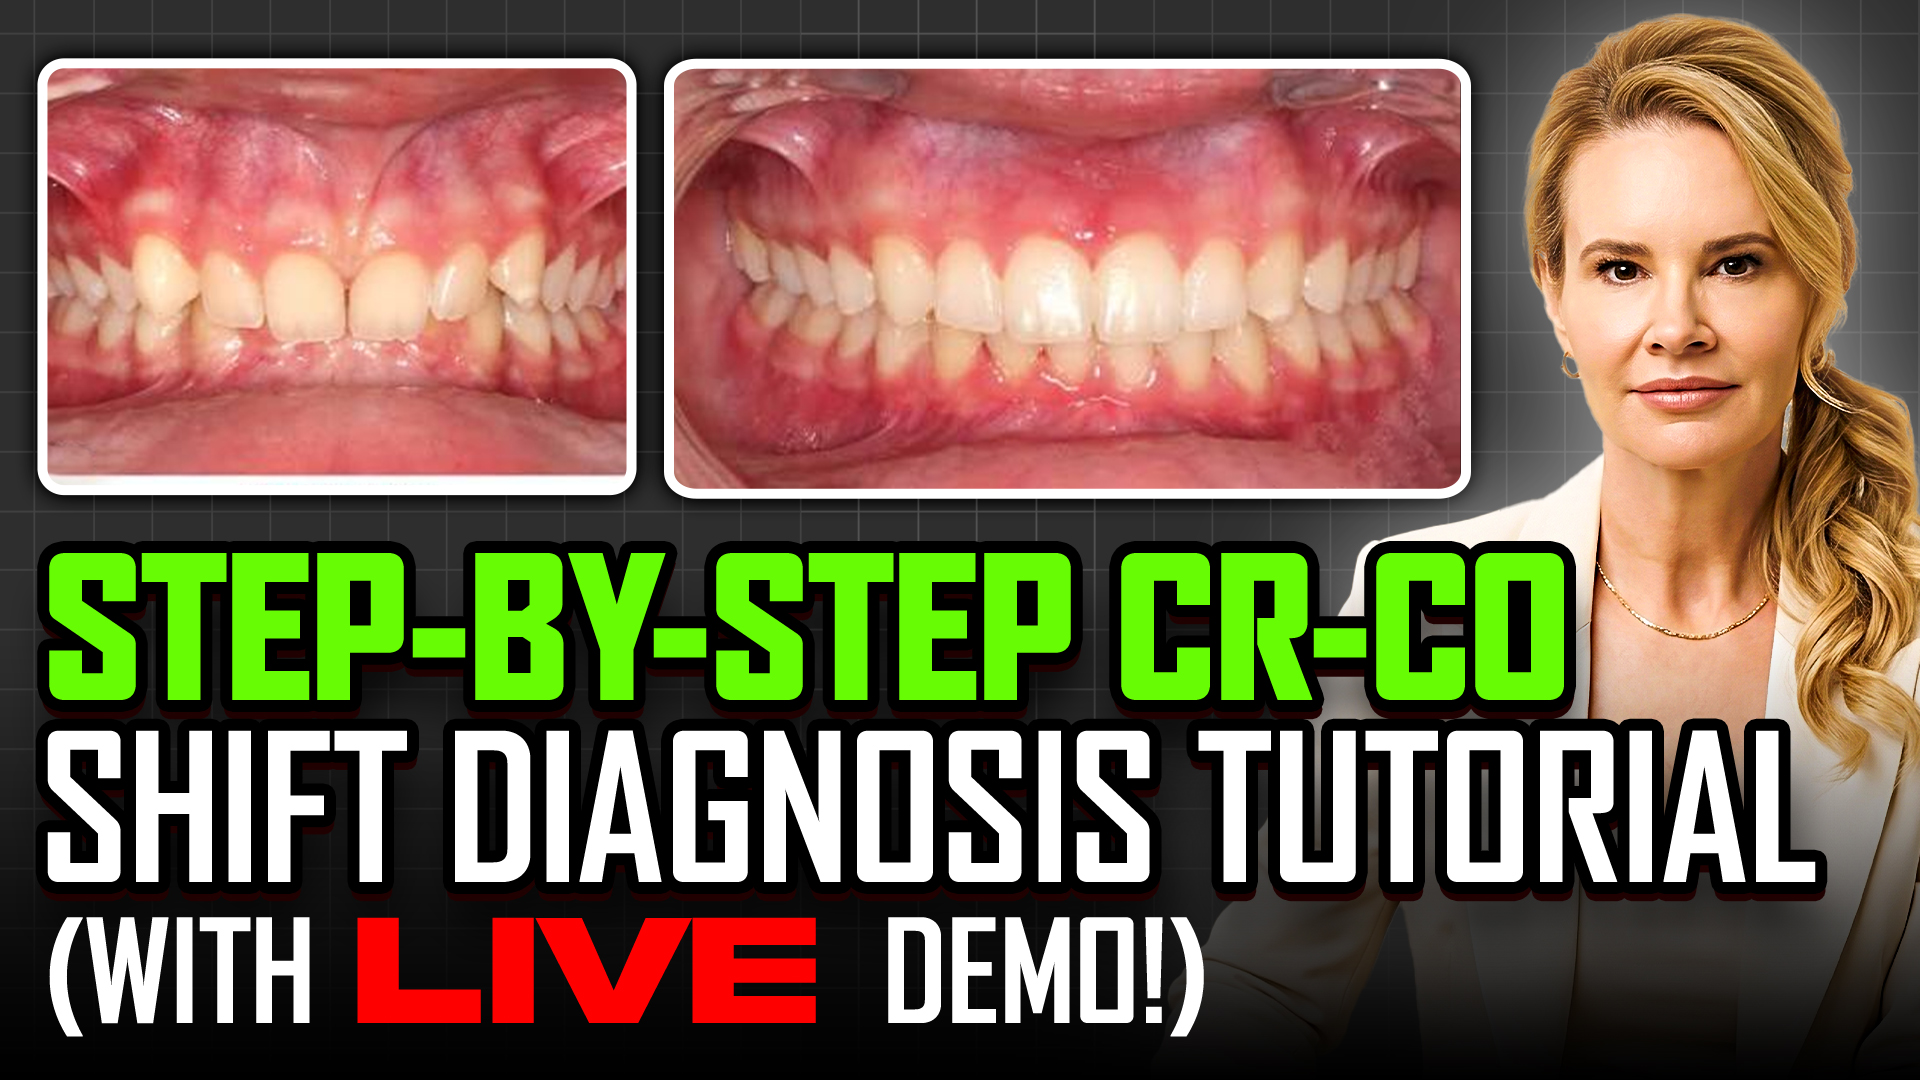
Diagnosing CR-CO Functional Shifts in Orthodontic Patients

Properly identifying a centric relation to centric occlusion functional shift is one of the most critical steps in planning accurate orthodontic treatment. When a patient presents with an interference, their jaw naturally shifts to find a comfortable chewing position. In class three patients, an edge-to-edge bite can trigger a forward shift that mimics a severe underbite. Failing to catch this shift can lead to major clinical errors, such as over-treating the patient with unnecessary jaw surgeries or extractions when simple interproximal reduction would have sufficed.

Furthermore, taking cephalometric radiographs in centric occlusion instead of centric relation will yield inaccurate numbers, compromising the entire treatment foundation.The risk is equally high for class two patients, though it often manifests differently. These patients may naturally slide their jaw forward due to muscle memory from elastics or functional appliances. Some younger patients even intentionally slide forward to trick the clinician into thinking their treatment is finished so they can get their appliances removed.

If you accept this “Sunday bite” as a true correction, the class two relationship will seemingly reappear weeks later. This is not a true relapse, but rather an uncorrected bite that was misdiagnosed.To prevent these errors, clinicians can guide young children by instructing them to make their jaw feel like jello. For older patients, a highly effective technique involves using Myospots to accurately guide the jaw. By placing one of these specialized lozenges as far back on the roof of the mouth as comfortable, you give the patient a precise target for the tip of their tongue. Once the tongue is held firmly against the spot, instruct the patient to close their jaw until they feel the very first point of contact. This technique effectively prevents the jaw from sliding, allowing you to accurately evaluate the true baseline bite, take reliable records, and build a safe, stable orthodontic plan.

Formulating a Strategic Orientation for Posterior Box Elastics

In comprehensive orthodontic treatment, settling the posterior occlusion is a key component of a stable clinical outcome. Clinicians frequently use posterior box elastics to vertically express teeth and establish solid maximum intercuspation. While the choice of elastic size and force level is highly critical, configuring the precise vector orientation of these elastics is equally vital for avoiding unintended side effects during the mechanics phase.
Biomechanics in Leveling vs. Finishing Stages
The behavioral requirements for elastic vectors shift dramatically across the different stages of fixed appliance therapy:
Leveling and Aligning Stage: Introducing light vertical box elastics early in treatment primarily serves to accelerate leveling arches and settling mild vertical gaps. At this point, clinicians typically use light forces ranging from two to three ounces. Because the force levels are minimal, slight variations in vector orientation rarely produce adverse dental movements, making precise orientation less critical during this initial phase.
Finishing and Detailing Stage: During the final treatment phase, mechanics change as heavy wires are engaged and heavy settling forces of six to six and a half ounces are deployed. Because these significant force levels are applied to complete the case, incorrect vector orientation can rapidly cause unwanted tooth movement or disrupt a coordinated canine relationship. Clinicians must verify the precise anchor teeth using articulating paper before finalizing the elastic configuration.
Coordinating Vectors with Anteroposterior Profiles
To achieve optimal finishing intercuspation, the directional force of the heavy elastic must match the patient’s existing anteroposterior skeletal blueprint:
Class One Profiles: For patients with properly coordinated skeletal and dental bases, box elastics should be worn in a strictly vertical direction. This orientation provides direct extrusion to close posterior open bites without introducing problematic horizontal forces.
Class Two Profiles: If a mild Class Two relationship persists into the finishing phase, the box elastic should feature a dedicated Class Two force vector. Angling the elastic forward from the lower molars to the upper premolars or canines helps settle the back teeth while simultaneously assisting with a final millimeter of overjet correction.
Class Three Profiles: For patients presenting a Class Three tendency, the exact opposite orientation must be prescribed. Running the vector forward from the upper arch to the lower arch creates a Class Three vector that pulls the lower dentition distally while extruding the posterior segment to achieve stable intercuspation.
To learn more about tailored orthodontic treatment planning or to submit a specific clinical inquiry, visit StraightSmile Solutions.

Formulating a Strategic Orientation for Posterior Box Elastics

In comprehensive orthodontic treatment, settling the posterior occlusion is a key component of a stable clinical outcome. Clinicians frequently use posterior box elastics to vertically express teeth and establish solid maximum intercuspation. While the choice of elastic size and force level is highly critical, configuring the precise vector orientation of these elastics is equally vital for avoiding unintended side effects during the mechanics phase.
Biomechanics in Leveling vs. Finishing Stages
The behavioral requirements for elastic vectors shift dramatically across the different stages of fixed appliance therapy:
Leveling and Aligning Stage: Introducing light vertical box elastics early in treatment primarily serves to accelerate leveling arches and settling mild vertical gaps. At this point, clinicians typically use light forces ranging from two to three ounces. Because the force levels are minimal, slight variations in vector orientation rarely produce adverse dental movements, making precise orientation less critical during this initial phase.
Finishing and Detailing Stage: During the final treatment phase, mechanics change as heavy wires are engaged and heavy settling forces of six to six and a half ounces are deployed. Because these significant force levels are applied to complete the case, incorrect vector orientation can rapidly cause unwanted tooth movement or disrupt a coordinated canine relationship. Clinicians must verify the precise anchor teeth using articulating paper before finalizing the elastic configuration.
Coordinating Vectors with Anteroposterior Profiles
To achieve optimal finishing intercuspation, the directional force of the heavy elastic must match the patient’s existing anteroposterior skeletal blueprint:
Class One Profiles: For patients with properly coordinated skeletal and dental bases, box elastics should be worn in a strictly vertical direction. This orientation provides direct extrusion to close posterior open bites without introducing problematic horizontal forces.
Class Two Profiles: If a mild Class Two relationship persists into the finishing phase, the box elastic should feature a dedicated Class Two force vector. Angling the elastic forward from the lower molars to the upper premolars or canines helps settle the back teeth while simultaneously assisting with a final millimeter of overjet correction.
Class Three Profiles: For patients presenting a Class Three tendency, the exact opposite orientation must be prescribed. Running the vector forward from the upper arch to the lower arch creates a Class Three vector that pulls the lower dentition distally while extruding the posterior segment to achieve stable intercuspation.
To learn more about tailored orthodontic treatment planning or to submit a specific clinical inquiry, visit StraightSmile Solutions.

Should You Fix Class 2 Overjet in a Non-Growing Adult?

Correcting a Class Two overjet in an adult patient requires deep diagnostic evaluation. Unlike growing children, adult patients present with fully consolidated skeletal structures that cannot be modified with standard growth modification appliances. Clinicians must weigh complex profile aesthetics, structural limitations, and underlying physiological factors before mapping out a definitive treatment plan.
Evaluating Skeletal Profiles and Airway Risks
In non-growing adult patients, a severe overjet is typically caused by a deficient, retruded mandible. Evaluating the facial profile utilizing the orthodontic E-line tool often highlights a significantly deficient chin position. Clinicians must exercise extreme caution when addressing these structural deficiencies.
Attempting to completely camouflage a skeletal problem by extracting upper premolars, executing heavy sequential distalization, or using aggressive interproximal reduction can pull the front teeth too far backward. This retraction can permanently collapse the tongue space, restrict the upper airway, and severely worsen undiagnosed obstructive sleep apnea. Therefore, comprehensive airway screenings must always occur before selecting a mechanical pathway.
Determining the Ideal Therapeutic Pathway
When severe skeletal or airway discrepancies exist, surgical jaw advancement remains the most appropriate medical resolution. Orthognathic surgery combined with traditional orthodontics coordinates the arches while fundamentally enlarging the restricted airway pathway. For patients who completely decline a surgical route, alternative camouflage plans must be heavily compromised.
Straightening the dental arches while safely leaving a structural overjet intact is a viable alternative to protect both facial profile aesthetics and airway health. Forcing the front teeth into a standard bite position through aggressive mechanical camouflage can introduce permanent speech defects, lisping, or irreversible profile flattening. Prioritizing overall health over artificial alignment keeps patients structurally safe and healthy.
To learn more about tailored orthodontic treatment planning or to submit a specific clinical inquiry, visit StraightSmile Solutions.


Why Traditional Pontics Complicate Braces Treatments
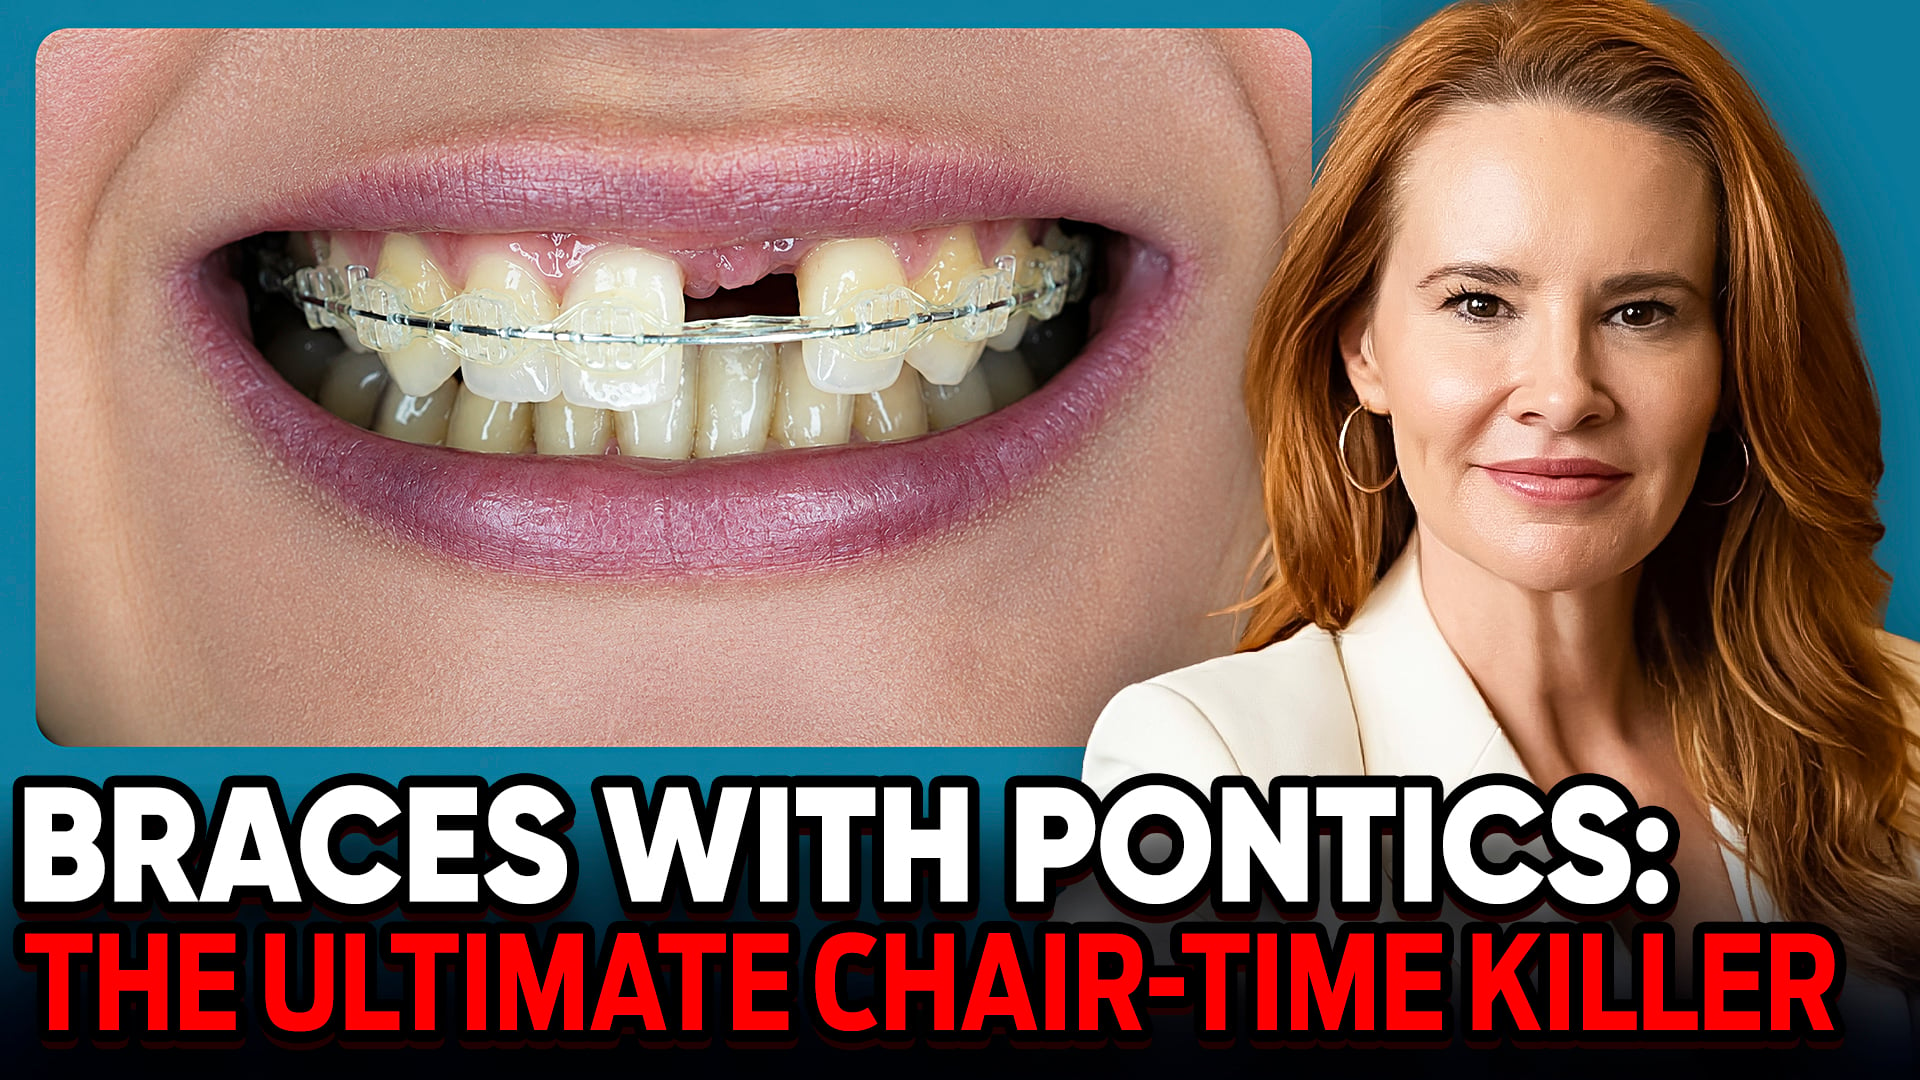
Why Traditional Pontics Complicate Braces Treatments
Managing missing anterior teeth during orthodontic treatment requires careful biomechanical planning. Historically, placing a temporary plastic tooth, or pontic, directly onto fixed braces was the standard method for maintaining aesthetics. However, modern clinical experience reveals that traditional pontics on braces introduce significant structural and logistical complications that can compromise practice efficiency and patient satisfaction.
The Technical Challenges of Fixed Brackets
Bonding a standard orthodontic bracket to a plastic denture tooth is a highly delicate and unstable process. Traditional composite materials are designed to adhere to natural enamel, not dental plastics, creating a weak interface prone to frequent debonding. To counteract this structural weakness, clinicians must create manual undercuts or mechanical retention points within the plastic tooth structure. Even with meticulous mechanical preparation, these assemblies experience high fracture rates during active treatment.
Furthermore, during the initial leveling and aligning stages, thin archwires lack the rigidity required to stabilize an unanchored plastic tooth. Because the pontic is not rooted in bone, the lightweight wires allow it to rotate, flip, or flex under normal chewing forces. This mobility frequently prompts patients to play with the appliance, accelerating structural failure and resulting in repetitive, unscheduled emergency appointments.
Operational Inefficiencies and Safety Risks
From a practice management standpoint, fixed pontics demand substantial chair time that cannot easily be billed to insurance. Every routine wire change requires the clinician to carefully untie, stabilize, and re-ligate the loose plastic tooth. This delicate process can easily result in the pontic dropping into the oral cavity or flying across the operatory.
Due to these severe technical limitations, clear aligner therapy serves as a far superior alternative for patients missing front teeth. Systems like Invisalign feature built-in, precisely contoured aesthetic spaces that remain highly stable throughout treatment. Transitioning these specific cases to clear aligner frameworks eliminates emergency bonding failures and significantly optimizes overall chairside productivity.
To learn more about tailored orthodontic treatment planning or to submit a specific clinical inquiry, visit StraightSmile Solutions.

Ceph Tracing: The Mandibular Angle Number That Means “Red Flag”- Low Angle, High Angle

Mandibular Plane Angle: Understanding Flat vs. Steep Growth Patterns
In interceptive orthodontics, reading a cephalometric analysis properly is vital for creating a successful treatment plan. One of the most telling numbers on a cephalometric tracing is the SN-GoGn mandibular plane angle. This specific metric identifies whether a patient possesses a flat or a steep mandibular growth trajectory. Recognizing these distinct skeletal patterns early allows clinicians to accurately predict how a patient’s jaw will grow and respond to different treatment mechanics.
Comparing Flat and Steep Skeletal Profiles
Each growth pattern presents unique structural characteristics and clinical implications:
Flat Mandibular Plane Angle: This framework is often characterized by a flat, low-angle face, a prominent chin, and heavy masseter muscles, resulting in a square-looking jawline. While this pattern can sometimes present alongside Class Two issues, it rarely occurs in Class Three cases. It is primarily genetic and generally stable, though it requires specific biomechanical management during alignment.
Steep Mandibular Plane Angle: This pattern presents a downward and backward mandibular growth trajectory, which often leads to an open bite or a Class Three skeletal relationship. When observed in a growing child, a steep angle acts as an immediate clinical red flag. This skeletal structure heavily correlates with vertical growth issues and underlying pediatric airway complications.
Addressing the Airway Connection
Discovering a steep mandibular plane angle in a pediatric patient requires prompt diagnostic action. Because this pattern frequently pairs with pediatric airway obstructions, clinicians must thoroughly investigate the upper respiratory system. Utilizing cephalometric X-rays to assess the adenoids, performing a tonsil analysis using standard formatting, and looking for signs of mouth breathing are essential steps. If airway obstructions are suspected, the provider must immediately coordinate referrals to an ear, nose, and throat specialist or a myofunctional therapist. Managing the airway obstacle first allows for a much more stable and predictable long-term orthodontic correction.
To learn more about tailored orthodontic treatment planning or to submit a specific clinical inquiry, visit StraightSmile Solutions.

How to Use a Lip Bumper in Interceptive Orthodontics

How to Use a Lip Bumper in Interceptive Orthodontics
In pediatric dentistry, addressing oral habits early can completely transform a child’s dental development. A common issue clinicians encounter in growing patients is the habit of lip sucking or lip biting. This repetitive pressure can severely disrupt the natural alignment of the teeth. Fortunately, incorporating a lip bumper into your orthodontic toolkit offers an elegant, highly effective solution for interceptive treatment.
Clinical Indications and Patient Selection
Lip bumpers are primarily utilized for young patients in the mixed dentition stage, typically ranging from seven to eleven years old. This interceptive window is ideal because the jaw is still growing and the permanent teeth are actively erupting. The appliance functions by creating a physical barrier that keeps the lower lip away from the lower teeth, effectively breaking the habit. Additionally, it harnesses the natural forces of the surrounding musculature to maintain or gain arch length, reducing the overall complexity of future orthodontic needs.
Laboratory Workflows and Delivery
When integrating these appliances into your practice, the fabrication method matters. Standard over-the-counter kits require manual measurement and assembly with individual bands, wires, and plastic components, which can be tedious and time-consuming. To maximize clinical efficiency, taking a digital scan and sending it to a lab for a custom, pre-assembled, and soldered appliance is highly recommended.
Always verify that the laboratory solders the appliance fully so it arrives ready for delivery.
Once the custom appliance arrives, the standard clinical workflow involves placing spacers a few days before delivery to create adequate room for the bands. The lip bumper is then securely seated and typically remains in place for four to six months. This timeframe provides sufficient time to successfully eliminate the oral habit. While some clinicians combine this with upper arch expanders or limited braces, a lip bumper on its own remains a powerhouse for standalone Phase One treatment.
To learn more about tailored orthodontic treatment planning or to submit a specific clinical inquiry, visit StraightSmile Solutions.