
StraightSmile Solutions®

The Wide-Smile Flex: Why Expanders Crush Aligner Tipping for a Full Smile


Have you ever noticed how some smiles look incredibly wide and full, while others have dark, empty corners? In the online aesthetic world, achieving that ultra-wide smile is a major part of “looksmaxing.” In a recent breakdown, Dr. Amanda from Straight Smile Solutions revealed the secret behind that perfect look: the battle between palatal expanders and standard aligners.To prove the point, she shared a case study of full siblings who started with very similar crowding. One sibling received a Rapid Palatal Expander (RPE) around age seven or eight, followed by Invisalign. The other sibling skipped the expander and only used aligners.The visual difference? Night and day. The sibling who had the expander achieved a beautiful, broad smile with zero dark spaces in the corners of their mouth.So, why can’t aligners just do the same thing? It all comes down to anatomy. True palatal expansion physically moves the two skeletal shelves of the palate apart using an RPE. This alters the actual bone structure, but it must be done early while the child is still growing. On the other hand, tooth tipping only widens a smile by pushing the teeth outward without changing the underlying bone. Waiting until a patient is older means missing out on that true skeletal expansion.Parents are now demanding expanders more than ever just for the aesthetic perks. While doctors still need a valid medical or orthodontic reason to use one—like crowding or a high palate—catching it early is the ultimate cheat code for a wider smile.

Elastic Anarchy: Why Guessing Your Rubber Band Sizes Is Ruining Your Results

Selecting the right diameter and strength of orthodontic elastics is one of the most poorly understood mechanics in general dentistry. Too many doctors treat the rubber band drawer like a guessing game, grabbing random sizes based on habit rather than physics. Whether you are running intermaxillary elastics for braces or executing precision cuts for clear aligners, guessing your elastic geometry will rapidly stall your tooth movement, create unwanted reciprocal side effects, and extend treatment times indefinitely.
To get your forces right, you have to look at the math behind diameter and strength. Orthodontic elastics are classified by their lumen diameter—ranging from tiny 1/8-inch bands up to wide 3/8-inch options—and their force delivery, typically categorized as light, medium, or heavy. The golden rule of mechanics is that an elastic delivers its stamped force rating only when it is stretched exactly three times its manufactured diameter. If you stretch a short band too far, the excessive force will overload the anchorage, dumping the molars or flaring the incisors. Conversely, if your chosen diameter is too large for the distance span, the force will drop below the biological threshold required to trigger bone remodeling.
Your archwire selection must fully support the elastic force you want to apply. If you attempt to run a Class II or Class III vector using heavy elastics on a flexible, low-dimension leveling wire like a 0.014 NiTi, the wire will bend under the strain, causing severe side effects like roller-coaster archwires and unwanted bite deepening. You should only run light or medium elastics once you have stepped up to a medium-sized wire, and reserve heavy elastics exclusively for rigid, full-slot rectangular stainless steel wires. Stop guessing with the rubber band sizes; calculate the structural span distance, match it to the three-times stretch rule, and protect your mechanics.

The Aligner Switch Myth: Why Rushing Tray Changes Will Ruin Your Outcomes
Choosing the perfect clear aligner brand for your practice is only half the battle; the real trick to clinical predictability lies in mastering your wear schedule protocols. A dangerous trend is sweeping through general dentistry where providers automatically default every clear aligner patient to an ultra-fast seven-day tray rotation. While major manufacturers like Invisalign push one-week changes as a standard selling point to attract fast-moving patients, treating this marketing guideline as a hard clinical rule across the board is a recipe for tracking failure, posterior open bites, and endless mid-course refinements.
The truth is that aligner tray frequency must be completely customized to the individual biological response of your patient and the specific tracking software being utilized. When you look at alternative white-label options or brands like ClearCorrect, they often leave the exact wear frequency entirely up to the discretion of the treating doctor, which can range anywhere from seven days to a full two weeks. A seven-day wear cycle only succeeds under perfect clinical conditions: the patient must be hitting a mandatory twenty-two hours of daily compliance, and you must see zero signs of lag or air gaps between the plastic and the incisal edges.
If you rush a patient to the next aligner tray before the periodontal ligament has fully remodeled and the surrounding bone has stabilized, the minor tracking errors will compound. By tray ten, the teeth will completely stop tracking, forcing you into a costly and time-consuming revision. To keep your treatment plans predictable, start your patient on a conservative ten-day or two-week wear schedule. Only consider dropping them down to a seven-day cycle if they demonstrate flawless compliance, use acceleration devices or remote monitoring systems, and show absolutely zero lag in tooth movement at their progress checks.

Ceph Secrets: Stop Confusing the Gonial Angle With the Mandibular Plane Angle


A massive wave of confusion is circulating across dental message boards and forums regarding basic cephalometric landmarks. General and pediatric dentists frequently confuse the gonial angle with the mandibular plane angle. While both are critical concepts for mapping out skeletal architecture, mixing them up will completely ruin your understanding of how a patient’s face grows and reacts to treatment. If you are tracking skeletal progress, it is vital to know exactly which metrics matter—and which ones are completely out of your hands.
The gonial angle is a structural measurement tracking the specific shape of the mandible itself. It represents the internal relationship of the mandibular ramus to the mandibular body. This angle is primarily dictated by genetics and is fixed to the physical blueprint of the bone structure the patient was born with. A common question popping up is whether palatal expansion will alter the gonial angle. The short answer is absolutely not. You cannot modify the innate shape of the mandibular bone through basic expansion mechanics.
The mandibular plane angle, however, is a completely different story. Measured via landmarks like Sella-Nasion to Gonion-Gnathion (GoGn-SN), this angle establishes how the jaw rests relative to the stable cranial base. An acute angle signals a favorable, forward-growing horizontal growth pattern, while an obtuse, steep angle indicates down-and-backward vertical growth, frequently hinting at an underlying airway obstruction. Because the mandible functions on a dynamic hinge axis, palatal expansion can tilt the maxillary denture base, causing a clockwise rotation of the mandible. This rotational change opens the hinge and directly alters your mandibular plane angle. When analyzing a growing interceptive case, stop wasting your energy staring at the structural gonial angle; keep your focus locked on tracking the mandibular plane angle to ensure your expansion therapy does not inadvertently throw your patient’s vertical growth out of control.

The Malpractice Trap: The True Risks of Camouflage Ortho (Airway, Profile, & Liability!)

Camouflage Orthodontics: Why Hiding a Bad Bite Could Destroy Your Patient’s Airway
In modern dental practices, “camouflage” orthodontics is a colloquial term we use when a patient presents with a severe skeletal jaw discrepancy, but a perfect orthognathic correction is off the table. Whether due to severe financial limitations, lack of insurance coverage, or a simple refusal to undergo invasive jaw surgery, doctors often pivot to a compromise plan. The core objective of a camouflage strategy is to shift, tilt, or extract teeth to make the dental arches align and occlude properly. However, while the teeth themselves might look beautifully straight at the conclusion of treatment, this approach merely masks an uncorrected skeletal imbalance at its source.
When you choose to camouflage a Class III skeletal pattern—where a prominent lower jaw creates a sagittal discrepancy—you typically extract lower premolars to retract the mandibular incisors. Clinicians must realize that while this stabilizes the occlusion, moving the lower dentition backward often drags the lower lip with it. This backward movement frequently accentuates the skeletal disharmony facially, leaving the patient with a seemingly larger chin profile than before.
The true clinical danger, however, lies in executing a camouflage plan for a skeletal Class II patient. Unlike Class III profiles, a Class II discrepancy is almost always caused by a deficient, retrognathic mandible rather than a massive maxilla. Decades ago, restricting the upper jaw with aggressive headgear was standard practice. Today, trying to camouflage Class II cases by pulling the upper teeth backward or extracting upper premolars to match a tiny lower jaw shrinks the functional intraoral volume. This drastic reduction compromises tongue space, restricts the upper airway, and directly increases the patient’s long-term risk for obstructive sleep apnea. Instead of using camouflage methods that permanently flatten a profile, focus on growth modification techniques or formal surgical referrals to protect your patient’s systemic health.

Bite Turbos vs. Posterior Bumps: The Secret Weapon for Quick Orthodontic Corrections


Deep bites and anterior crossbites present significant challenges in a standard orthodontic setup. Left unmanaged, patients will repeatedly bite down on their lower brackets, causing constant breakages, treatment delays, and immense frustration for both the clinician and the patient. To bypass this issue and unlock faster tooth movement, you must strategically use anterior bite turbos or posterior bite bumps to temporarily alter the patient’s vertical dimension.
For severe deep bites, placing an appliance like a fixed bite plate supported by the palate or adding anterior bite turbos to the lingual surfaces of the front teeth is highly effective. This mechanic immediately prevents full closure, allowing the posterior teeth to erupt freely and leveling the curve of Spee, which can be accelerated by box or triangle elastics once you transition into larger wires. However, because the force concentrates heavily on the anterior segment, you must exercise extreme caution. Avoid placing anterior turbos on patients with a history of dental trauma or short roots, as the intensive localized force can widen the periodontal ligament space and exacerbate structural root vulnerabilities.
When your primary clinical objective is to quickly jump an anterior or posterior crossbite, temporary posterior bite bumps are the superior tool. By stacking composite on the occlusal surfaces of the molars or premolars, you slightly lift the occlusion so tucked teeth can slide forward without getting locked behind the lower arch. The danger with posterior bumps lies in leaving them on too long, which causes the supporting teeth to intrude over several months, resulting in an iatrogenic posterior open bite. To prevent this, limit their use to a short window of one to two months and tint the composite a subtle blue using primer mixed with blue articulating paper. This simple visual cue ensures your team will never mistake a lumpy, worn-down temporary bump for a standard composite filling, reminding you to drill it away completely the moment the crossbite clears.

The Open Bite Trap: Why Elastics Alone Won’t Save You From a Lawsuit


Closing an anterior open bite can feel like a major clinical victory, but if you rush to fix it with braces and elastics without understanding the root cause, you are walking into an orthodontic trap. Open bites do not just happen out of nowhere. They are heavily driven by underlying skeletal structural issues, airway obstructions, tongue thrusts, or stubborn childhood habits like prolonged pacifier use and thumb sucking. If you fail to identify and treat the root etiology first, the bite will relapse post-treatment—no matter how many bonded retainers you place.
Before you even think about ordering elastics, you must screen the patient’s airway and check for a myofunctional tongue thrust. If the open bite is skeletal in nature or extends past the canines into a posterior open bite, orthodontic treatment alone will fail. These patients require complex orthognathic jaw surgery. If your patient refuses surgery and wants to try an orthodontic-only approach, they must sign a formal clinical compromise form. Documenting that the patient was informed of the risks and alternatives protects your practice from immense liability when the bite inevitably attempts to relapse.
For mild, isolated canine-to-canine open bites where the underlying habits are fully corrected, you can utilize an anterior box or trapezoid elastic setup. However, geometry only works if your wire sequence is stable. Never jump the gun on light wires. You need to complete your leveling and aligning first, reaching at least a medium NiTi wire before applying medium elastics via Kobashis (Kobi hooks) on the lateral incisors. If you have progressed the patient into heavy rectangular wires, you can safely step up to heavy forces. Just remember: open bites are highly unstable, and your long-term success hinges on a mandatory canine-to-canine bonded retainer covered by an Essix overlay.

Fire Your Front Desk? Why a Virtual Dental Assistant is Your Next Big Growth Engine


The traditional dental clinic staffing model is broken, and if you are still trying to force your physical clinical team to handle both in-office mechanics and the booming demand for virtual care, you are capping your practice’s growth. Most doctors confuse remote billing or front-office scheduling teams with a true Virtual Dental Assistant. A true virtual assistant does not manage phone lines or claims—they manage your back-office clinical pipeline, shifting the heavy lifting of patient monitoring completely out of your physical chairs.
Bringing a virtual assistant onto your team unlocks massive efficiency, specifically for scaling up high-margin, removable orthodontic treatments. Whether your practice is focused on Invisalign, ClearCorrect, sleep appliances, retention checks, or Phase 1 growth appliances, these patients do not actually need to sit in your chair every few weeks unless an emergency arises. By using HIPAA-compliant remote platforms like Inhand Dental, your virtual assistant can handle asynchronous check-ins, reviewing patient-submitted selfies to confirm aligners are tracking properly, checking elastic wear, and tracking retention progress.
This model is a massive win for both your overhead and your staff retention. Talented dental assistants are actively seeking better compensation, flexibility, and an improved quality of life. Shifting a proven clinician—like a trusted office manager or lead assistant who needs remote flexibility—into a virtual clinical role preserves your office culture while opening up a brand-new operational pipeline. They can safely screen data, manage virtual consults, and seamlessly escalate true issues directly to you. Stop wasting expensive chair time on simple visual compliance checks; hire a virtual clinical assistant, free up your physical team, and scale your production.

Invisalign vs. ClearCorrect: Choosing the Right Aligner Brand for Your Dental Practice


As a general or pediatric dentist, one of the questions you will face almost daily from both patients and peers is how Invisalign stacks up against ClearCorrect and the hundreds of other alternative clear aligner brands popping up across the globe. While it can be tempting to focus purely on the lab fees, selecting the right clear aligner brand requires a deeper look at the actual clinical features, physical materials, and overall value.
When you evaluate Invisalign and ClearCorrect side-by-side, the physical differences are immediate. ClearCorrect aligners utilize a significantly more rigid plastic material, and the trim line is cut differently than Invisalign’s scalloped approach. Rigidity and trim lines are not inherently superior or inferior; rather, they present unique pros and cons depending on the specific biomechanical objectives of your case.
Beyond the base materials, the software capabilities and automated features differ. Invisalign offers built-in precision cuts directly from the factory, which allow you to easily attach rubber bands for complex movements. With ClearCorrect, you can still use elastics, but you have to manually cut the aligners yourself, adding a layer of clinical hassle. Invisalign also features highly customized, branded attachment shapes tailored for specific tooth movements, whereas ClearCorrect offers a slightly more simplified, traditional template.
However, ClearCorrect shines in its cost-efficiency features for the provider. They include free retainers for the dentist at the end of treatment, which represents a massive direct value that you would otherwise have to absorb or purchase as an add-on with Invisalign. For a straightforward, middle-of-the-road case, you can comfortably utilize a more generic aligner brand, save significantly on lab fees, and pass those savings directly onto your patient. But if you encounter a highly complex or challenging case, going cheap will backfire. Understanding your specific case complexity and matching it to the right aligner brand is the true key to clinical predictability.

The Open Coil Spring Mistake: Why Wire Selection Can Make or Brea
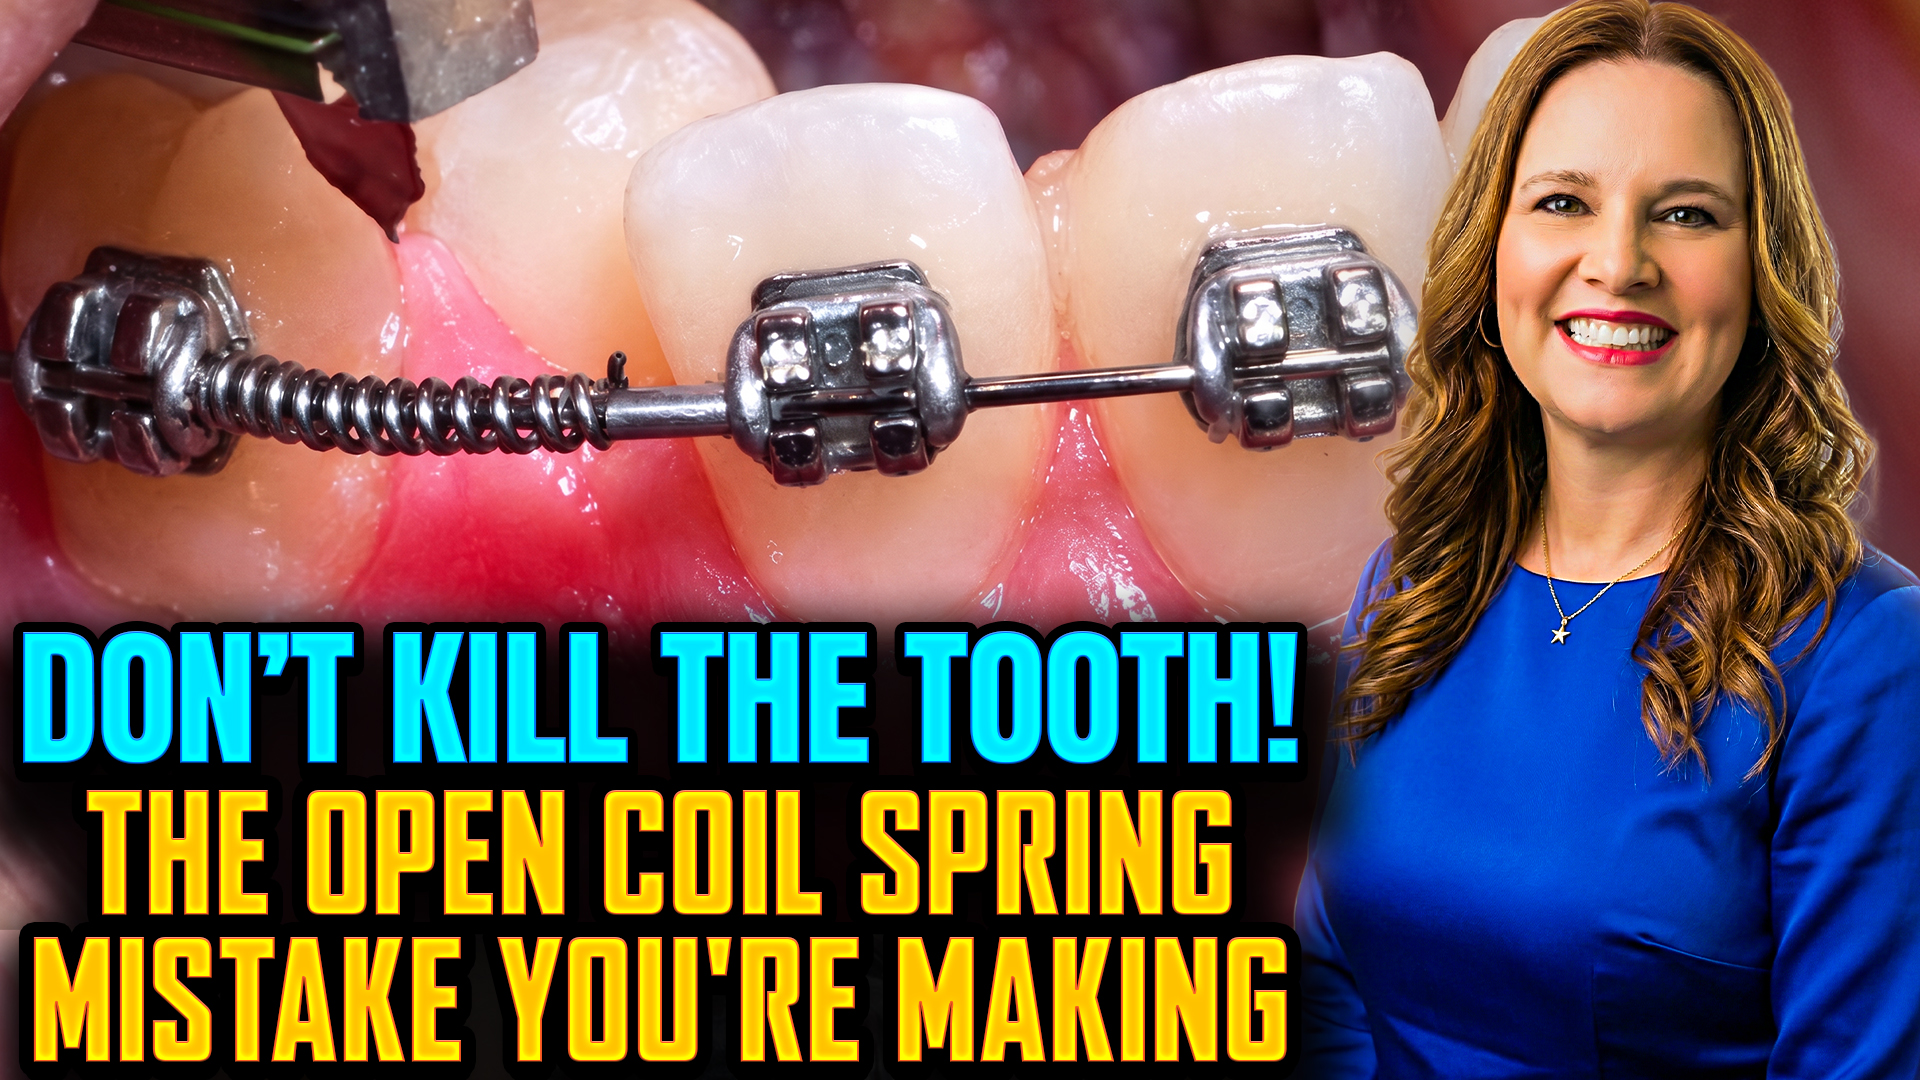
Open coil springs are fantastic orthodontic tools for gaining space or uprighting molars, but using them incorrectly can easily derail your treatment plan. One of the most common mistakes general and pediatric dentists make is rushing to place an open coil spring on the wrong type or size of archwire. If you place a spring on a wire that is too light, you risk completely losing control of the teeth. 

The first rule of thumb is material choice. You should always select nickel-titanium (NiTi) open coil springs rather than stainless steel. NiTi possesses a shape memory that delivers a gentle, continuous force, which works infinitely better for space creation. 

The second rule is all about filling the bracket slot. Many standard orthodontic courses show pictures of springs on light, round wires, but in practice, this creates a major issue called “slop.” If you place a spring on a light round wire inside a standard 0.022 bracket slot, the force will cause the adjacent teeth to rotate radically, often flaring mesial out. Left unmonitored, this excessive, uncontrolled force can push teeth right through the buccal plate, causing fenestration, periodontal issues, and even pulp devitalization. 

To prevent this, you must be patient and wait until you are on a heavy rectangular wire that fills the slot. For a 0.022 bracket slot, your absolute minimum wire should be an 18×25 or a 19×25. If your practice uses a 0.018 bracket slot, the smallest wire you should use is a 17×25. Fully filling the bracket slot guarantees the necessary torque and stability to handle the spring’s force safely, keeping your treatment predictable and your patients safe.